


Öz
Orthostatic intolerance represents a broad clinical continuum encompassing orthostatic hypotension (OH) and postural orthostatic tachycardia syndrome (POTS). Although both entities share overlapping manifestations, such as dizziness, presyncope, and palpitations, their underlying autonomic mechanisms differ substantially. Distinguishing between these disorders is crucial yet often diagnostically challenging, particularly in older adults and those with multimorbidity. We report the case of a 78-year-old woman with recurrent episodes of dizziness and presyncope, initially suspected to have orthostatic hypotension and possible arrhythmic etiology. During active standing, her heart rate increased by more than 30 bpm without a significant fall in blood pressure, fulfilling diagnostic criteria for POTS. Continuous 24-hour Holter electrocardiography revealed a tachycardic response to orthostasis without arrhythmogenic events. Comprehensive cardiovascular, neurological and endocrine evaluations were unremarkable, excluding secondary causes of orthostatic intolerance such as anemia, hypovolemia, endocrine disorders, or structural heart disease. The patient’s symptoms improved markedly with non-pharmacological measures, gradual mobilization and low-dose beta-blocker therapy. This case underscores the diagnostic complexity within the orthostatic intolerance spectrum and highlights the need for meticulous assessment of autonomic responses. OH and POTS may appear clinically similar but differ fundamentally in pathophysiology. OH is characterized by impaired vasoconstriction and an inadequate, often blunted heart rate response due to autonomic dysfunction, whereas POTS involves excessive sympathetic activation with a pronounced tachycardic response. Recognition of POTS in the older adults is critical, as misclassification can delay management. Comprehensive autonomic testing and individualized therapy remain key to optimizing outcomes.
Anahtar Kelimeler: Orthostatic hypotension, postural orthostatic tachycardia syndrome, orthostatic intolerance, autonomic dysfunction, older adults
Introduction
Orthostatic intolerance encompasses a diverse range of autonomic disorders marked by symptoms of reduced cerebral blood flow, including dizziness, palpitations, dyspnea, presyncope and syncope upon assuming the upright position. The two most clinically significant conditions in this spectrum are orthostatic hypotension (OH) and postural orthostatic tachycardia syndrome (POTS), which exhibit similar symptoms but differ greatly in their fundamental pathophysiology.[1] Orthostatic hypotension, defined as a sustained reduction of systolic blood pressure (SBP) ≥ 20 mmHg or diastolic blood pressure (DBP) ≥ 10 mmHg within 3 minutes of standing (with measurements taken at 1 and 3 minutes) or during head-up tilt, primarily due to impaired baroreflex-mediated sympathetic activation that results in inadequate vasoconstriction, reduced vascular resistance, and an insufficient heart rate (HR) response to postural change.[1,2] It predominantly occurs in older adults, patients with neurodegenerative disorders, diabetes, or drug-induced autonomic failure, and is associated with an increased risk of falls, cardiovascular events, and mortality.[3] In contrast, POTS is defined by a HR increase of ≥ 30 beats per minute (≥ 40 beats per minute in adolescents) within 10 minutes of standing without orthostatic hypotension, usually indicating hyperadrenergic activation, hypovolemia, or peripheral denervation.[4] Although their underlying mechanisms differ, these syndromes may clinically overlap, posing significant diagnostic challenges.
POTS is often overlooked in older adults because it is traditionally regarded as a condition of younger individuals, while orthostatic symptoms in this population are more commonly attributed to age-related autonomic dysfunction, comorbidities, polypharmacy, or classical orthostatic hypotension, leading to under recognition despite fulfillment of diagnostic criteria.[3-5]
Given that even experienced clinicians seldom encounter both conditions concurrently, and considering their overlapping features that can obscure clinical interpretation, we present a case illustrating the diagnostic complexity between OH and POTS. This case report not only underscores the difficulty of differentiating these entities in practice but also provides deeper insight into their shared and divergent autonomic mechanisms, clinical characteristics, and therapeutic implications.
Case Presentation
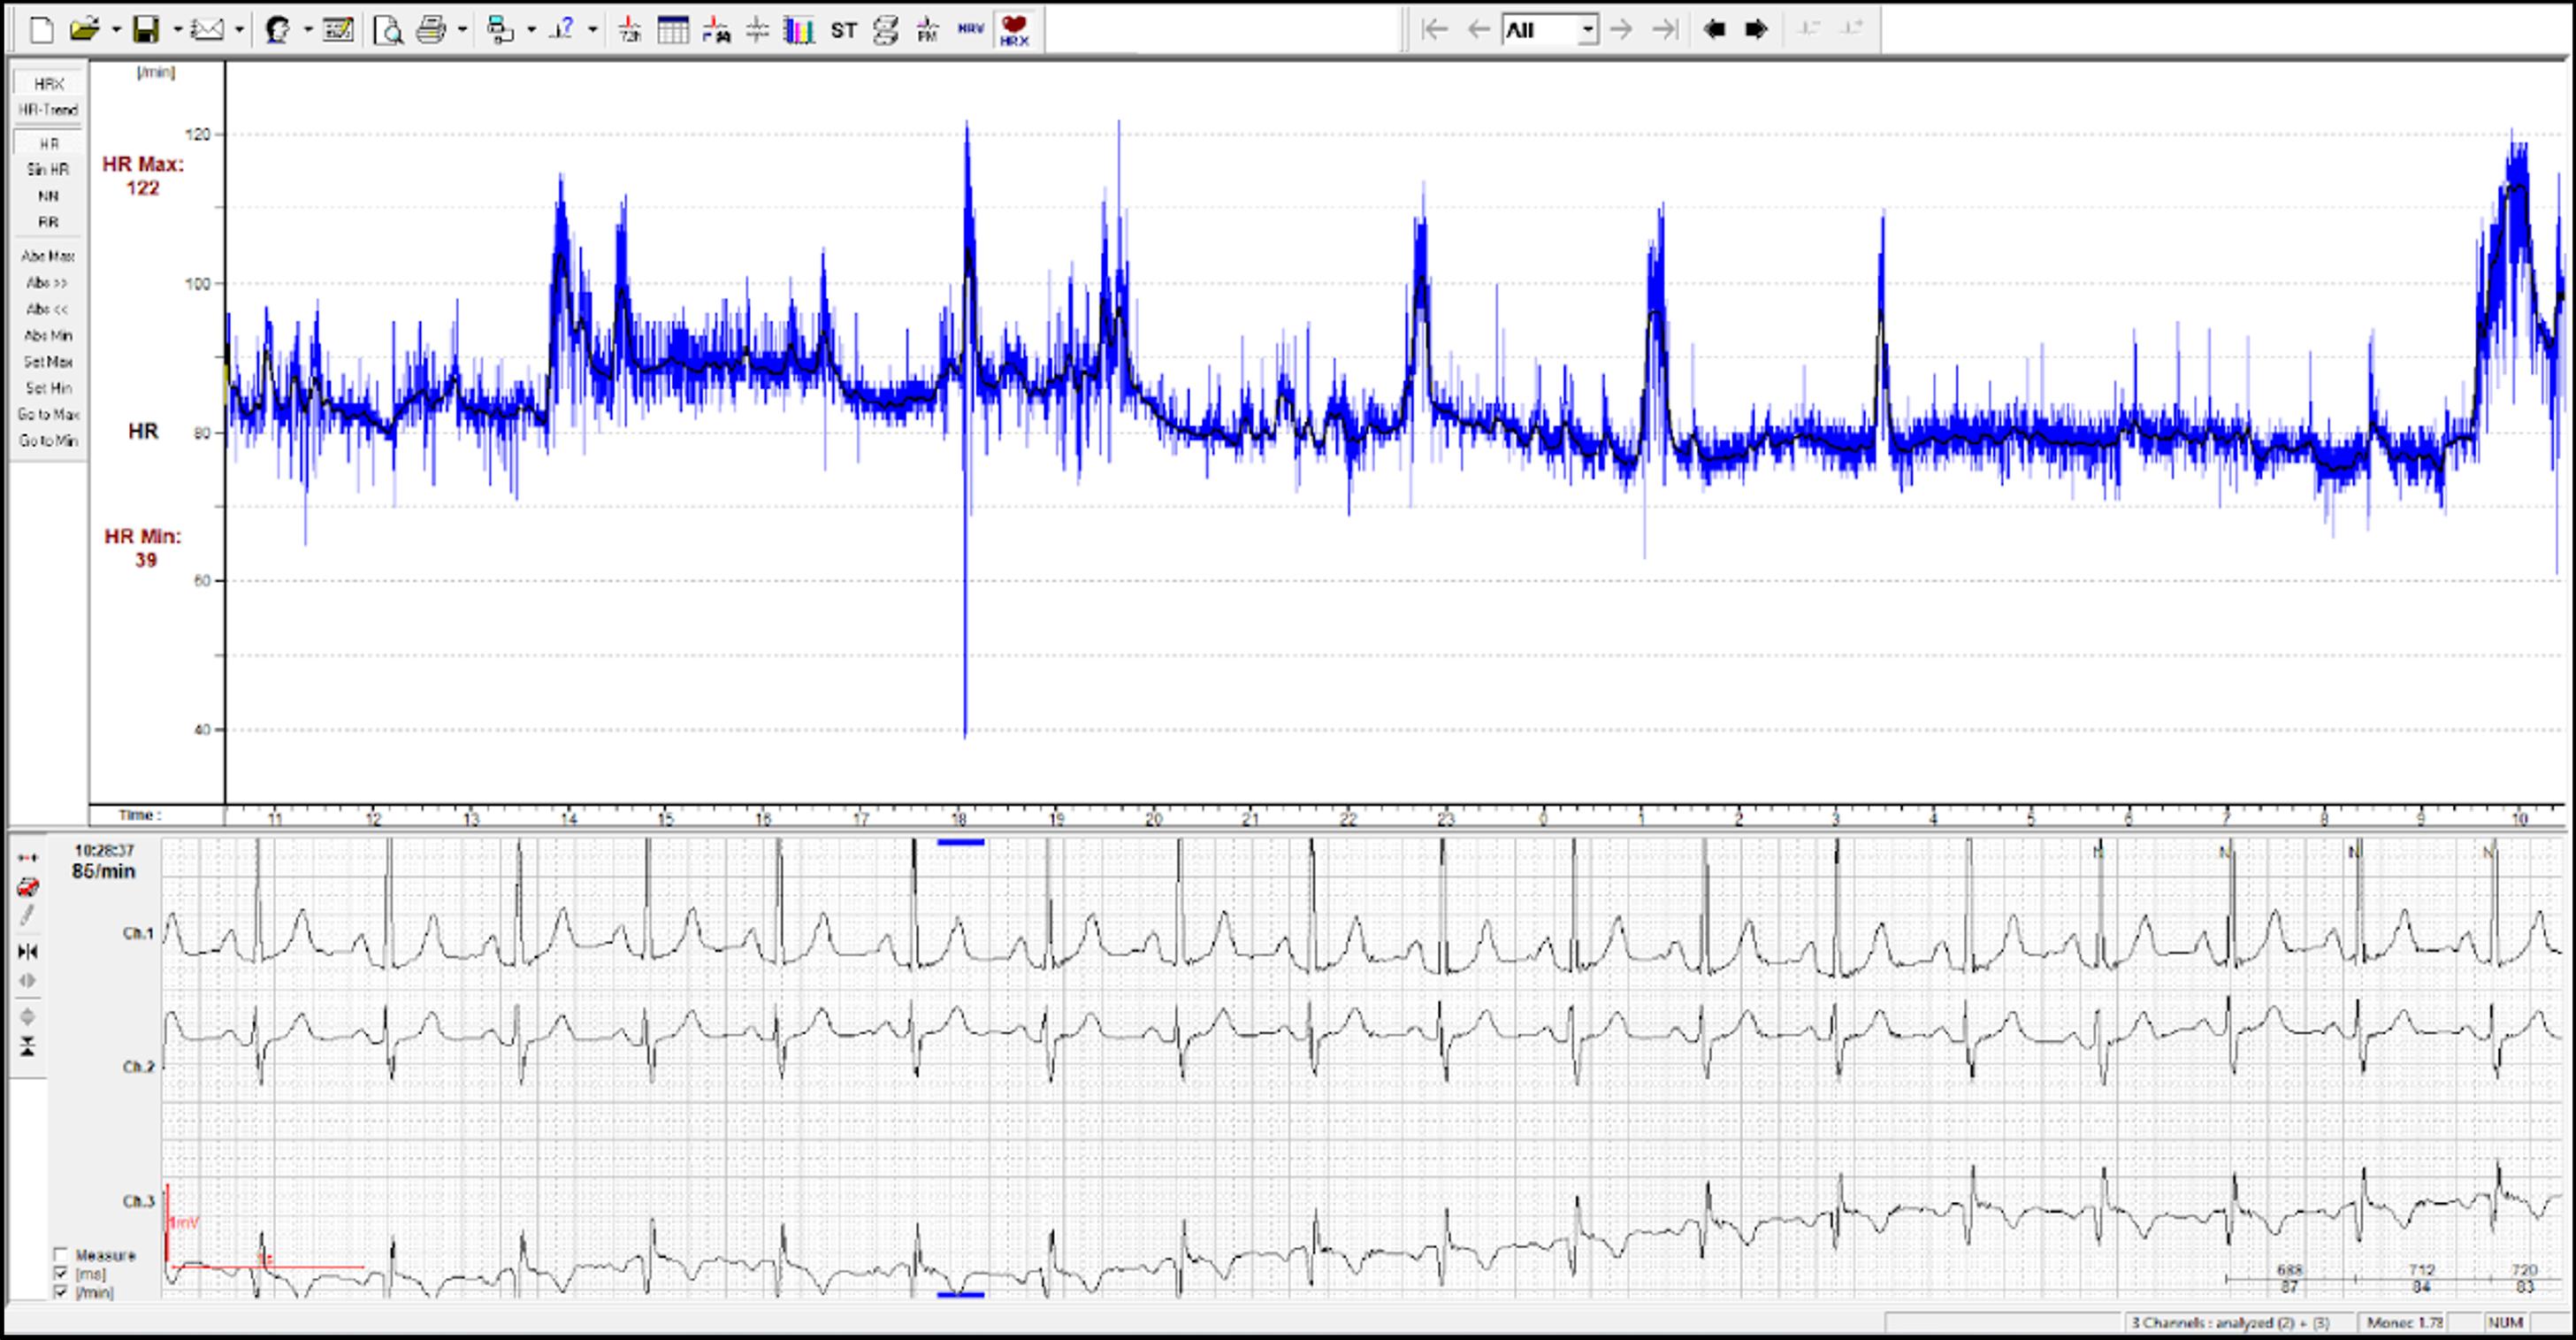
A 78-year-old woman was admitted for evaluation of recurrent episodes of palpitations, dyspnea, and symptoms of orthostatic intolerance. Following hospital discharge in June 2023, she experienced daily attacks lasting several minutes, typically triggered by standing or initiating physical activity. The episodes were characterized by sudden weakness, visual dimming, a sensation of impending fainting, and marked palpitations, described as a "flopping heart". The symptoms resolved spontaneously upon sitting or lying down, after which she felt profoundly fatigued and often slept for several hours. She noticed that very slow positional changes alleviated her symptoms. Her past medical history was unremarkable apart from mild, well-controlled asthma until she was diagnosed with lung adenocarcinoma (pathological stage pT1c pN0 R0, indicating a primary tumor measuring between 2 and 3 cm, without nodal involvement and with clear resection margins), treated with a right lower lobectomy in 2020. In 2022, she underwent right-sided pneumonectomy for recurrence, followed by 30 sessions of radiotherapy and three cycles of platinum-pemetrexed chemotherapy, during which she involuntarily lost 20 kg. In April 2023, she developed pneumonia complicated by empyema and septic shock, requiring prolonged intensive care, mechanical ventilation, and treatment for critical illness neuromyopathy. After prolonged treatment in the intensive care unit (ICU), she was successfully extubated and transferred to the pulmonology department for respiratory and locomotor rehabilitation. However, at that time, she remained profoundly weak and bedridden, and due to her frailty and multiple comorbidities, the treating physicians considered her prognosis extremely poor and decided that, in the event of clinical deterioration, reintubation or invasive ventilation would not be appropriate. Nevertheless, her condition gradually improved with supportive care and rehabilitation. After discharge, inpatient rehabilitation was initiated but interrupted because of the recurrence of orthostatic episodes. On readmission, her general condition had improved compared to the period following her ICU stay, though she exhibited reduced muscle tone and diminished exercise tolerance. Supine blood pressure (BP) was normal, and bedside orthostatic testing revealed no significant drop in BP, while there was a marked tachycardic response upon standing. Orthostatic vital signs are summarized in Table 1. The orthostatic test was repeated several times and was consistently symptomatic, reproducing the patient’s complaints of dizziness, palpitations, and presyncope, with a reproducible HR increase without hypotension. Echocardiography demonstrated preserved left ventricular systolic function and mild diastolic function without structural abnormalities. 24-hour Holter electrocardiogram (ECG) confirmed abrupt HR increases during standing and ambulation, without arrhythmic events, though mild excess of supraventricular ectopic beats was noted (Figure 1). Laboratory evaluation excluded anemia, electrolyte imbalance, and endocrine disorders. On the basis of the patient’s clinical features and bedside orthostatic assessment OH was ruled out, while the pronounced tachycardic response met diagnostic criteria for POTS. Treatment focused on non-pharmacological strategies, including adequate fluid and salt intake, nutritional support to promote gradual weight gain, use of elastic compression stockings, and cautious positional changes, along with gradual beta-blocker titration (bisoprolol). Individualized physiotherapy and progressive mobilization were also implemented. Over the following weeks, the patient demonstrated significant symptomatic improvement, and at one-year follow up she remained asymptomatic and functionally independent, with only mild limitations during strenuous exertion, having returned to regular daily exercise and independent driving.
| HR: heart rate; BP: blood pressure. | ||||
| Table 1. Orthostatic vital signs. Supine and orthostatic blood pressure and heart rate measurements, showing preserved blood pressure and a marked heart rate increase on standing, consistent with POTS without orthostatic hypotension. | ||||
| Time point |
|
|
|
Notes |
| Supine (baseline) |
|
|
|
Normal baseline |
| 1 minute standing |
|
|
|
Marked tachycardia, no hypotension |
| 3 minutes standing |
|
|
|
Posture-related symptoms: dizziness, palpitations |
| 10 minutes standing |
|
|
|
Presyncope during prolonged standing; resolves on sitting |
Discussion
Orthostatic intolerance encompasses a broad spectrum of hemodynamic disturbances that arise from impaired autonomic regulation during the transition from a supine to an upright posture. Differentiating OH from POTS in practice is often challenging, even for experienced clinicians, due to overlapping symptoms such as dizziness, presyncope, palpitations, and generalized weakness (Table 2).[5] Current consensus guidelines distinguish OH by a sustained decrease in SBP of ≥ 20 mmHg or DBP of ≥ 10 mmHg within 3 minutes of standing, reflecting impaired baroreflex-mediated vasoconstriction.[6] In contrast, POTS is characterized by an excessive increase in HR of ≥ 30 beats per minute within 10 minutes of standing in the absence of significant OH, typically indicating excessive sympathetic activation and/or relative hypovolemia.[7] These criteria provide a useful diagnostic framework, although real-world differentiation is frequently complicated by overlapping symptoms and mixed autonomic phenotypes.
| HR: heart rate; BP: blood pressure. | ||
| Table 2. Key Distinctions Between Orthostatic Hypotension and Postural Orthostatic Tachycardia Syndrome. Adapted from reference.[2,4,16,17] | ||
| Parameter | Orthostatic Hypotension (OH) | Postural Orthostatic Tachycardia Syndrome (POTS) |
| Typical age group | Predominantly older adults | More frequent in younger women |
| Pathophysiology | Impaired baroreflex-mediated sympathetic vasoconstriction, venous pooling and reduced vascular resistance | Excessive sympathetic activation, relative hypovolemia and impaired venous return |
| Hemodynamic response | Drop in BP with absent or minimal HR increase | Stable BP with marked HR increase (≥30 beats per minute) within 10 min of standing |
| Typical signs and symptoms | Dizziness, blurred vision, fatigue, presyncope, weakness on standing | Palpitations, tremor, dyspnea, cognitive “fog,” exercise intolerance |
| Electrocardiographic and hemodynamic findings | BP drop, mild or absent HR increase | Sustained sinus tachycardia without hypotension or arrhythmia |
| Common triggers | Rapid standing, dehydration, warm environment, antihypertensive drugs | Prolonged standing, heat exposure, postprandial state, hormonal changes |
From a pathophysiological perspective, OH results from inadequate baroreflex-mediated sympathetic vasoconstriction with venous pooling in splanchnic and lower extremity circulations, leading to reduced venous return and a consequent drop in arterial pressure. Although a compensatory increase in HR normally accompanies vasoconstriction, this chronotropic response is blunted or insufficient in neurogenic OH (ΔHR/ΔSBP < 0.5 beats per minute/mmHg), reflecting impaired sympathetic outflow, whereas in non-neurogenic OH the HR response is preserved or exaggerated.[5-7]
Although physiologically distinct, OH and POTS frequently overlap in clinical practice, particularly among older adults or critically ill patients, where partial autonomic dysfunction, cardiovascular deconditioning, hypovolemia, or medication effects may coexist.[8]
Moreover, bedside orthostatic testing is frequently suboptimal, often performed without adequate supine rest or standardized timing of measurements, leading to underrecognition of POTS or misclassification as OH. Accurate diagnosis requires standardized hemodynamic assessment following 5–10 minutes of supine rest, with serial recordings during active standing or head-up tilt testing at 1, 3, and 10 minutes.[9] In older adults, diagnostic interpretation is further complicated by blunted baroreceptor sensitivity, polypharmacy, and reduced vascular compliance, as well as by limited mobility and poor physical conditioning, which may hinder adequate performance of active standing tests.[8-10] Additionally, medications commonly used in this population, including antihypertensives, diuretics, and antidepressants may further confound hemodynamic responses.[10]
In the present case, the patient’s history of critical illness, prolonged immobilization, and neuromyopathic weakness likely contributed to secondary autonomic dysfunction and marked cardiovascular deconditioning. Furthermore, cumulative effects of chemotherapy, radiotherapy, and concurrent effects of chemotherapy, radiotherapy and concomitant medications may have exacerbated autonomic instability and blunted baroreceptor responsiveness, thereby obscuring the classical distinction between OH and POTS. Despite advanced age, multiple comorbidities, and extensive thoracic surgery, the hemodynamic profile revealed a pronounced tachycardic response upon standing without a significant fall in BP, consistent with a POTS pattern rather than neurogenic or hypovolemic hypotension. This observation highlights that postural tachycardia can occur even in older, frail individuals, particularly following prolonged critical illness or major thoracic procedures that disrupt autonomic homeostasis.[11,12] Interpretation of orthostatic responses in such patients is inherently complex, as physiological aging diminishes baroreceptor sensitivity and vascular compliance, while polypharmacy and systemic deconditioning further modulate hemodynamic adaptation.[12]
In this patient, additional factors, including critical illness neuromyopathy, significant weight loss, and prior exposure to vasodilatory and chemotherapeutic agents most likely compounded autonomic dysfunction, resulting in an atypical presentation within the orthostatic intolerance spectrum. This intermediate phenotype, characterized by tachycardia without hypotension, underscores the need for meticulous hemodynamic assessment and nuanced diagnostic reasoning rather than reliance on rigid categorical criteria.[13] Comprehensive evaluation, including active standing testing and 24-hour Holter monitoring, was pivotal in identifying the predominant mechanism and excluding reversible causes such as anemia, dehydration, or endocrine dysfunction. The hemodynamic pattern of isolated tachycardia with preserved BP supported a diagnosis consistent with POTS and guided an appropriate, targeted management strategy.[14] Therapeutic intervention focused on re-establishing autonomic balance through non-pharmacologic measures, such as adequate hydration and salt intake, compression therapy, and gradual mobilization, combined with low-dose beta-blocker therapy for symptomatic tachycardia.[14,15] The patient’s progressive recovery and sustained symptom resolution over one year underscore the importance of early recognition and individualized care in post-critical illness dysautonomia.
Management of orthostatic intolerance requires a tailored, pathophysiology-guided approach based on the patient's hemodynamic profile. Accurate differentiation between OH and POTS is essential, as therapeutic strategies differ substantially (Table 3). In OH, treatment aims to restore effective circulating volume and maintain cerebral perfusion through correction of hypovolemia, withdrawal of precipitating medications, use of compression garments, and, when indicated, pharmacologic agents such as midodrine, droxidopa, or fludrocortisone.[3,8,15] Conversely, management of POTS focuses on attenuating excessive sympathetic activation and improving venous return. Non-pharmacologic measures, including adequate fluid and salt intake, compression therapy, gradual mobilization, and structured physical reconditioning form the cornerstone of therapy, while pharmacologic interventions such as beta-blockers, ivabradine, or low-dose midodrine are reserved for persistent or severe symptoms.[5,7,16]
| SBP: systolic blood pressure; DBP: diastolic blood pressure; BP: blood pressure; HR: heart rate. | ||
| Table 3. Key Diagnostic and Therapeutic Approach in Orthostatic Hypotension and Postural Orthostatic Tachycardia Syndrome. Adapted from reference.[3,5,7,8,15,16] | ||
| Assessment / Action | Findings Suggestive of Orthostatic Hypotension | Findings Suggestive of Postural Orthostatic Tachycardia Syndrome |
| Clinical assessment | Dizziness, presyncope, blurred vision, weakness on standing; associated with diabetes and/or neurodegenerative disease | Palpitations, tremor, fatigue, 'brain fog,' exercise intolerance; associated with autoimmune disorders or post-viral syndromes |
| Active standing or tilt test | Decrease of SBP ≥20 mmHg or DBP ≥10 mmHg within 3 minutes; absent or blunted compensatory HR increase | Increase of HR ≥30 beats per minute (≥40 in adolescents) within 10 minutes of standing; without orthostatic hypotension (no SBP drop ≥20 mmHg or DBP drop ≥10 mmHg) |
| Confirmatory or supportive testing | Beat-to-beat BP monitoring | 24-h Holter ECG |
| Therapeutic strategy | Volume repletion, salt intake, compression garments, midodrine or fludrocortisone | Fluid and salt loading, compression, graded exercise, β-blocker or ivabradine (if needed) |
| Follow-up | Evaluate BP stability, risk of falls, renal and cardiovascular outcomes | Monitor HR control, exercise tolerance, and symptom improvement |
Misclassification between these entities may lead to iatrogenic harm. For example, vasopressors may aggravate tachycardia in POTS, whereas inappropriate beta-blockade in OH may precipitate syncope. Therefore, precise diagnostic confirmation and individualized treatment planning are critical to achieving optimal clinical outcomes.[17] In the present case, the exclusion of secondary causes, together with a favorable response to volume expansion, graded rehabilitation, and low-dose beta-blocker therapy, supported the diagnosis of a functional autonomic disturbance and consistent with POTS and underscored the importance of a personalized, dynamically adjusted management approach.
This case illustrates several key aspects of orthostatic intolerance in older adults. First, it demonstrates how systematic, hemodynamically guided evaluation can prevent misclassification between OH and POTS. An initial assumption of OH was revised following active standing testing and 24-hour Holter ECG monitoring, which revealed a tachycardic response without a corresponding BP fall, consistent with POTS.
Second, it highlights how secondary autonomic impairment following major thoracic surgery, critical illness, severe deconditioning, and muscle mass loss can produce a mixed or transitional phenotype, blurring the traditional distinction between OH and POTS. Recent studies have described such atypical phenotypes, especially in older or frail patients, where overlapping mechanisms complicate the clinical picture.[18,19]
Third, the case demonstrates that meaningful functional recovery is achievable even in advanced age when therapy is individually tailored. In this patient, non-pharmacologic interventions, graded rehabilitation, and cautious low-dose pharmacotherapy resulted in durable symptom remission. Finally, the broader implication is that clinicians should view orthostatic intolerance as a continuum rather than a set of rigid categories. In older adults, it often represents a multifactorial condition where autonomic impairment, polypharmacy, sarcopenia, and cardiovascular deconditioning coexist. Early recognition through structured orthostatic assessment and hemodynamically guided interpretation is essential to prevent misdiagnosis and inappropriate therapy. Individualized, multidimensional management, incorporating medication review, tailored rehabilitation, and targeted non-pharmacologic strategies, may substantially reduce the risk of falls, recurrent hospitalizations, and functional decline, ultimately improving overall quality of life.[20] A multidisciplinary approach integrating geriatric, cardiologic, and autonomic expertise should therefore represent the cornerstone of care in such complex clinical scenarios.
This case highlights that orthostatic intolerance in older adults represents a fluid continuum rather than distinct entities such as OH or POTS. Precise hemodynamic assessment and individualized, targeted management based on the underlying pathophysiological mechanisms are essential for achieving favorable outcomes. Even in older frail patients recovering from critical illness, restoration of autonomic stability through structured rehabilitation and carefully tailored pharmacotherapy can lead to meaningful functional recovery and sustained symptom control. Such an approach underscores the importance of comprehensive and individualized care in managing autonomic dysfunction in older frail patients.
Ethical approval
Written informed consent for publication of this case report has been obtained from the patient and is available upon request.
Source of funding
The authors declare the study received no funding.
Conflict of interest
The authors declare that there is no conflict of interest to disclose.
Referanslar
- Ricci F, De Caterina R, Fedorowski A. Orthostatic hypotension: epidemiology, prognosis, and treatment. J Am Coll Cardiol. 2015;66(7):848-860. https://doi.org/10.1016/j.jacc.2015.06.1084
- Freeman R, Abuzinadah AR, Gibbons C, Jones P, Miglis MG, Sinn DI. Orthostatic hypotension: JACC state-of-the-art review. J Am Coll Cardiol. 2018;72(11):1294-1309. https://doi.org/10.1016/j.jacc.2018.05.079
- Mol A, Bui Hoang PTS, Sharmin S, et al. Orthostatic hypotension and falls in older adults: a systematic review and meta-analysis. J Am Med Dir Assoc. 2019;20(5):589-597. https://doi.org/10.1016/j.jamda.2018.11.003
- Fedorowski A. Postural orthostatic tachycardia syndrome: clinical presentation, aetiology and management. J Intern Med. 2019;285(4):352-366. https://doi.org/10.1111/joim.12852
- Ruzieh M, Grubb BP. Orthostatic intolerance and postural tachycardia syndrome: new insights into pathophysiology and treatment. Herzschrittmacherther Elektrophysiol. 2018;29(2):183-186. https://doi.org/10.1007/s00399-018-0563-1
- Low PA. Neurogenic orthostatic hypotension: pathophysiology and diagnosis. Am J Manag Care. 2015;21(13 Suppl):248-257.
- Wells R, Spurrier AJ, Linz D, et al. Postural tachycardia syndrome: current perspectives. Vasc Health Risk Manag. 2017;14:1-11. https://doi.org/10.2147/VHRM.S127393
- Dani M, Dirksen A, Taraborrelli P, et al. Orthostatic hypotension in older people: considerations, diagnosis and management. Clin Med (Lond). 2021;21(3):e275-e282. https://doi.org/10.7861/clinmed.2020-1044
- Brignole M, Moya A, de Lange FJ, et al. 2018 ESC Guidelines for the diagnosis and management of syncope. Eur Heart J. 2018;39(21):1883-1948. https://doi.org/10.1093/eurheartj/ehy037
- Zia A, Kamaruzzaman SB, Tan MP. Blood pressure lowering therapy in older people: does it really cause postural hypotension or falls? Postgrad Med. 2015;127(2):186-193. https://doi.org/10.1080/00325481.2015.996505
- Vernino S, Bourne KM, Stiles LE, et al. Postural orthostatic tachycardia syndrome (POTS): state of the science and clinical care from a 2019 National Institutes of Health Expert Consensus Meeting - Part 1. Auton Neurosci. 2021;235:102828. https://doi.org/10.1016/j.autneu.2021.102828
- Bryarly M, Phillips LT, Fu Q, Vernino S, Levine BD. Postural orthostatic tachycardia syndrome: JACC focus seminar. J Am Coll Cardiol. 2019;73(10):1207-1228. https://doi.org/10.1016/j.jacc.2018.11.059
- Raj SR, Bourne KM, Stiles LE, et al. Postural orthostatic tachycardia syndrome (POTS): priorities for POTS care and research from a 2019 National Institutes of Health Expert Consensus Meeting - Part 2. Auton Neurosci. 2021;235:102836. https://doi.org/10.1016/j.autneu.2021.102836
- Ghazal M, Akkawi AR, Fancher A, et al. Pathophysiology and management of postural orthostatic tachycardia syndrome (POTS): a literature review. Curr Probl Cardiol. 2025;50(3):102977. https://doi.org/10.1016/j.cpcardiol.2024.102977
- Narasimhan B, Aggarwal D, Satish P, Kantharia B, Aronow WS. Postural orthostatic tachycardia syndrome: pathophysiology, management, and experimental therapies. Expert Opin Investig Drugs. 2022;31(10):1017-1025. https://doi.org/10.1080/13543784.2022.2121697
- Raj SR, Fedorowski A, Sheldon RS. Diagnosis and management of postural orthostatic tachycardia syndrome. CMAJ. 2022;194(10):E378-E385. https://doi.org/10.1503/cmaj.211373
- Raj SR, Guzman JC, Harvey P, et al. Canadian cardiovascular society position statement on postural orthostatic tachycardia syndrome (pots) and related disorders of chronic orthostatic intolerance. Can J Cardiol. 2020;36(3):357-372. https://doi.org/10.1016/j.cjca.2019.12.024
- Fedorowski A, Ricci F, Hamrefors V, et al. Orthostatic hypotension: management of a complex, but common, medical problem. Circ Arrhythm Electrophysiol. 2022;15(3):e010573. https://doi.org/10.1161/CIRCEP.121.010573
- Jordan J, Biaggioni I, Kotsis V, et al. Consensus statement on the definition of orthostatic hypertension endorsed by the American Autonomic Society and the Japanese Society of Hypertension. Clin Auton Res. 2023;33(1):69-73. https://doi.org/10.1007/s10286-022-00897-8
- Michon PL, Kahn JE, Picart C, Cudennec T, Pepin M. Orthostatic hypotension: focus on a common pathology sometimes misknowned. Geriatr Psychol Neuropsychiatr Vieil. 2022;20(4):421-428. https://doi.org/10.1684/pnv.2022.1063
Telif hakkı ve lisans
Telif Hakkı © 2026 Yazar(lar). Açık erişimli bu makale, orijinal çalışmaya uygun şekilde atıfta bulunulması koşuluyla, herhangi bir ortamda veya formatta sınırsız kullanım, dağıtım ve çoğaltmaya izin veren Creative Commons Attribution License (CC BY) altında dağıtılmıştır.



